
nur für Forschungszwecke
Moxifloxacin (BAY12-8039) HCl Topoisomerase Inhibitor
Kat.-Nr.: S1465
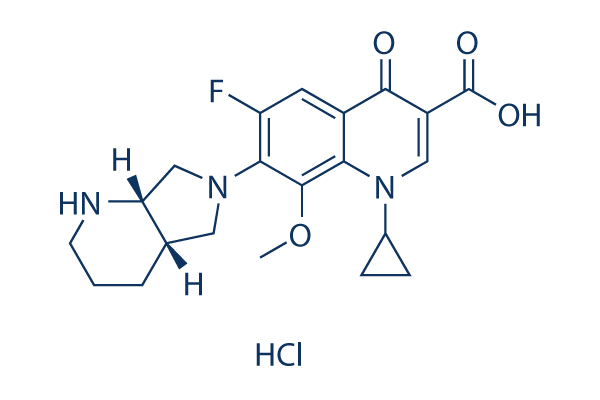
Chemische Struktur
Molekulargewicht: 437.89
Qualitätskontrolle (Quality Control)
| Verwandte Ziele | HDAC PARP ATM/ATR DNA-PK WRN DNA/RNA Synthesis PPAR Sirtuin Casein Kinase eIF |
|---|---|
| Weitere Topoisomerase Inhibitoren | Camptothecin (CPT) Betulinic acid (S)-10-Hydroxycamptothecin Beta-Lapachone Ellagic acid Amonafide Voreloxin (SNS-595) hydrochloride Hydroxy Camptothecine Cu(II)-Elesclomol 7-Ethylcamptothecin |
Chemische Informationen, Lagerung & Stabilität (Chemical Information, Storage & Stability)
| Molekulargewicht | 437.89 | Formel | C21H24FN3O4.HCl |
Lagerung (Ab dem Eingangsdatum) | |
|---|---|---|---|---|---|
| CAS-Nr. | 186826-86-8 | SDF herunterladen | Lagerung von Stammlösungen |
|
|
| Synonyme | Avelox, Avalox,BAY12-8039 HCl | Smiles | COC1=C2C(=CC(=C1N3CC4CCCNC4C3)F)C(=O)C(=CN2C5CC5)C(=O)O.Cl | ||
Löslichkeit (Solubility)
|
In vitro |
DMSO
: 88 mg/mL
(200.96 mM)
Water : 18 mg/mL Ethanol : Insoluble |
Molaritätsrechner
|
In vivo |
|||||
In-vivo-Formulierungsrechner (Klare Lösung)
Schritt 1: Geben Sie die untenstehenden Informationen ein (Empfohlen: Ein zusätzliches Tier zur Berücksichtigung von Verlusten während des Experiments)
Schritt 2: Geben Sie die In-vivo-Formulierung ein (Dies ist nur der Rechner, keine Formulierung. Bitte kontaktieren Sie uns zuerst, wenn es im Abschnitt "Löslichkeit" keine In-vivo-Formulierung gibt.)
Berechnungsergebnisse:
Arbeitskonzentration: mg/ml;
Methode zur Herstellung der DMSO-Stammlösung: mg Wirkstoff vorgelöst in μL DMSO ( Konzentration der Stammlösung mg/mL, Bitte kontaktieren Sie uns zuerst, wenn die Konzentration die DMSO-Löslichkeit der Wirkstoffcharge überschreitet. )
Methode zur Herstellung der In-vivo-Formulierung: Nehmen Sie μL DMSO Stammlösung, dann hinzufügenμL PEG300, mischen und klären, dann hinzufügenμL Tween 80, mischen und klären, dann hinzufügen μL ddH2O, mischen und klären.
Methode zur Herstellung der In-vivo-Formulierung: Nehmen Sie μL DMSO Stammlösung, dann hinzufügen μL Maisöl, mischen und klären.
Hinweis: 1. Bitte stellen Sie sicher, dass die Flüssigkeit klar ist, bevor Sie das nächste Lösungsmittel hinzufügen.
2. Achten Sie darauf, das/die Lösungsmittel der Reihe nach hinzuzufügen. Sie müssen sicherstellen, dass die bei der vorherigen Zugabe erhaltene Lösung eine klare Lösung ist, bevor Sie mit der Zugabe des nächsten Lösungsmittels fortfahren. Physikalische Methoden wie Vortex, Ultraschall oder ein heißes Wasserbad können zur Unterstützung des Lösens verwendet werden.
Wirkmechanismus (Mechanism of Action)
| Targets/IC50/Ki |
Topoisomerase II
Topoisomerase IV
|
|---|---|
| In vitro |
Moxifloxacin exerts its effects by trapping a DNA drug enzyme complex and specifically inhibiting ATP-dependent enzymes topoisomerase II (DNA gyrase) and topoisomerase IV. Moxifloxacin shows in-vitro potency against M. tuberculosis H37Rv with MIC of 0.177 μg/mL. Moxifloxacin has broad Grampositive and Gram-negative activity. Moxifloxacin shows in vitro and clinical efficacy against Staphylococcus aureus, Streptococcus pneumoniae, Str. pyogenes, Haemophilus influenzae, H. parainfluenzae, Klebsiella pneumoniae, Moraxella catarrhalis, Chlamydia pneumoniae and Mycoplasma pneumoniae. Moxifloxacin has activity against mycobacteria in addition to M. tuberculosis; Moxifloxacin is more active against M. kansasii than M. avium complex: specifically MIC90 for M. avium > M. intracellulare > M. kansasii at 4, 2 and 2 μg/mL, respectively. MIC90 for M. chelonae > M. fortuitum at 16 and 0.5 μg/mL, respectively. |
| In vivo |
Moxifloxacin combined with RIF/pyrazinamide (PZA) reduces treatment time by up to 2 months compared to regimens with isoniazid (INH)/RIF/PZA in a mouse model designed to mimic human disease. Similar results with a stable cure are reached after 4 months in mice treated twice weekly with RIF/Moxifloxacin/PZA compared to cure in 6 months when daily treated with RIF/INH/PZA. 100 mg/kg Moxifloxacin in mice gives activity comparable to INH; increased dose in mice to 400 mg/kg Moxifloxacin daily results in spleen CFU counts lower than for INH 25 mg/kg although the differences are not statistically significant. AUC/MIC ratio correlates best with in-vivo efficacy for the fluoroquinolones in a mouse model of tuberculosis. |
Literatur |
Klinische Studieninformationen (Clinical Trial Information)
(Daten von https://clinicaltrials.gov, aktualisiert am 2026-09-02)
| NCT-Nummer | Rekrutierung | Erkrankungen | Sponsor/Kooperationspartner | Startdatum | Phasen |
|---|---|---|---|---|---|
| NCT06441006 | RECRUITING | Tuberculosis, Pulmonary; Tuberculosis, Multidrug-Resistant; Tuberculosis, MDR |
University of California, San Francisco |
2025-10-03 | PHASE2; PHASE3 |
| NCT07485010 | NOT_YET_RECRUITING | Mycobacterium Abscessus Pulmonary Disease; Mycobacterium Abscessus Infection; Non-Tuberculous Mycobacterial (NTM) Infections; Non-Tuberculous Mycobacteria Pulmonary Disease |
The University of Queensland |
2027-04 | PHASE2 |
| NCT03244072 | NOT_YET_RECRUITING | Endophthalmitis |
Jason Ahee, M.D. |
2026-06-01 | PHASE2; PHASE3 |
| NCT04310930 | RECRUITING | Pulmonary Disease Due to Mycobacteria (Diagnosis) |
The University of Queensland |
2020-03-02 | PHASE2; PHASE3 |
| NCT07595042 | NOT_YET_RECRUITING | Tuberculosis |
National Institute of Allergy and Infectious Diseases (NIAID) |
2026-10-30 | PHASE2 |
| NCT07585461 | NOT_YET_RECRUITING | Opportunistic Infections, HIV Related; Disseminated Mycobacterium Avium Complex Infection |
Shanghai Public Health Clinical Center |
2026-04-30 |

Produkte sind nur für Forschungszwecke bestimmt. Nicht für den menschlichen Gebrauch. Wir verkaufen nicht an Patienten.
©Copyright 2013 Selleck Chemicals. Alle Rechte vorbehalten.